
Full vs Partial Dentures in Newmarket

If you are missing teeth in Newmarket, one of the first questions you will face is whether you need a full denture, a partial denture, or something else entirely. Understanding full vs partial dentures starts with a simple distinction: a full denture replaces every tooth in an arch, while a partial denture fills in gaps and works alongside the healthy natural teeth you still have. This guide compares the two honestly — how each works, how long each tends to last, what care they need, and who each one suits — so you can prepare for a proper assessment. Keeping healthy natural teeth, when they can be kept, is usually worth doing. Natural teeth hold jawbone in place and give a partial denture something stable to grip. But keeping teeth that are failing can mean repeated repairs and discomfort. The right choice depends on the condition of your remaining teeth, your gums and bone, and your general health. On this page What a full denture is What a partial denture is Full vs partial dentures: side-by-side comparison How to choose between a full and a partial denture Frequently Asked Questions What a full denture is A full (complete) denture is a removable appliance that replaces all the teeth in the upper arch, the lower arch, or both. The upper denture covers the roof of the mouth and is held in place largely by suction against the gums. The lower denture rests on the gum ridge and is held by the tongue and cheek muscles, which is why lower full dentures often take more practice to manage. You can read more about the options on our page covering dentures in Newmarket and how denture treatment is planned. A full denture is usually considered when the remaining teeth in an arch are too damaged, loose, or decayed to keep, or when they have already been lost. It restores appearance and basic chewing, although chewing force is lower than with natural teeth and some foods remain difficult. What a partial denture is A partial denture replaces one or more missing teeth while your remaining natural teeth stay in place. The appliance has a framework — acrylic, metal, or a combination — with false teeth attached, and it clips or rests against your natural teeth for support and stability. It is removable for cleaning and at night. A partial denture also helps stop neighbouring natural teeth from drifting into the gaps. It does depend on the health of the teeth it grips: if a supporting tooth is later lost, the partial usually needs to be adjusted, extended, or remade. General information about denture care is available from the Canadian Dental Association, and your dental team can explain the specifics for your appliance. Full vs partial dentures: side-by-side comparison Factor Full denture Partial denture What it is / how it works A removable appliance replacing every tooth in an upper or lower arch. It rests on the gums; the upper denture also covers the palate and is retained mainly by suction, the lower by the ridge and surrounding muscles. A removable appliance replacing some missing teeth in an arch. Its framework rests on the gums and clips or rests against the remaining natural teeth, which share the load and keep it stable. Typical lifespan Dentures do not last indefinitely. Rather than a fixed survival figure, the consistent finding in prosthodontic guidance is that fit changes over time as the jawbone and gums remodel after tooth loss, so dentures commonly need relining, adjustment, or replacement after a number of years of wear. Your dentist will review fit at regular check-ups and advise when replacement is due. The same applies to partial dentures: there is no single dependable lifespan figure, because fit and function change as gums remodel and as the supporting natural teeth change. Relines, repairs, and eventual replacement are a normal part of partial denture care over the years, and losing a supporting tooth often means the appliance must be remade. Maintenance and care Remove and clean the denture daily with a denture brush and a suitable cleanser, clean your gums and tongue, and soak the denture as directed. Leave it out overnight unless your dentist advises otherwise, and attend regular check-ups so fit and oral tissues can be examined. Remove and clean the partial daily, and brush and floss your natural teeth carefully — especially where the framework touches them, because plaque collects around clasps and raises the risk of decay in the supporting teeth. Leave the appliance out overnight and keep regular check-ups. Effect on neighbouring teeth and jawbone There are no neighbouring natural teeth in the arch. Without tooth roots, the jawbone under a full denture gradually shrinks over the years, which is the main reason fit loosens over time and relines become necessary. The remaining natural teeth are preserved, and their roots continue to hold bone around them. Bone still shrinks in the gaps where teeth are missing, and the supporting teeth take extra load and need careful cleaning to stay healthy. Who it suits and who it does not Often suits people who have lost all teeth in an arch, or whose remaining teeth in that arch cannot reasonably be saved. It is less suitable as a first step when several healthy teeth remain that could be kept for years. Often suits people with several healthy, stable natural teeth remaining who are missing some teeth in the same arch. It is less suitable when the remaining teeth are loose, heavily decayed, or likely to be lost soon, because the appliance depends on them. Number of visits and treatment timeline Usually several appointments over a few weeks: assessment and impressions, bite records, a try-in to check fit and appearance, then delivery and follow-up adjustments. If teeth still need to be removed first, healing time or an immediate denture plan changes the timeline. Usually several appointments over a few weeks: assessment of the supporting teeth, impressions, framework and bite checks, a
Crown vs Implant: How Newmarket Patients Decide

On this page The short answer Crown vs implant, side by side How to choose Common questions The short answer Crown vs implant is really two different questions wearing one name. A crown caps and protects a tooth that is still there. An implant replaces a tooth that is gone — root and all. If your tooth can be saved, the crown is usually the answer. If the tooth is missing or cannot be saved, the implant is what rebuilds it. This guide compares both for patients in Newmarket, including the common middle case: a crown that sits on top of an implant. For the full picture of replacement treatment, see dental implants in Newmarket. Crown vs implant, side by side Dental crown (on your own tooth) Dental implant (with its own crown) What it is / how it works A custom cap shaped like the original tooth, cemented over a prepared natural tooth to protect it and restore its shape. A small titanium post placed in the jawbone where the root used to be; after healing, a crown is attached on top of it. Typical lifespan Systematic reviews by Sailer, Pjetursson and colleagues report roughly 94% of metal-ceramic crowns surviving at 5 years (survival of the crown, not a promise for any single tooth); many crowns last well beyond that with normal care. Systematic reviews by Pjetursson and colleagues report 10-year survival around 95% for single implants and their crowns (survival of the implant/restoration). Individual results depend on bone, health and habits such as smoking. Maintenance and care Brush and floss normally, with care at the crown’s edge where it meets the gum. The tooth underneath can still decay, so check-ups matter. Brush and clean around the implant like a natural tooth, including under the crown edge; professional cleaning and periodic X-rays check the bone holding it. Effect on neighbouring teeth and jawbone The natural root stays, so the bone around it is preserved. Neighbouring teeth are not touched. The post stimulates the bone in the gap, which helps limit the bone shrinkage that follows tooth loss. Neighbouring teeth are not prepared, unlike a bridge. Who it suits — and who it does not Suits a tooth that is cracked, heavily filled, worn, or has had a root canal, but still has a sound root and enough structure. It cannot help a tooth that is missing or fractured through the root. Suits a missing tooth, or one that must come out, where there is enough bone (or bone can be rebuilt) and general health allows a minor surgical procedure. It may not suit uncontrolled medical conditions or heavy smoking without a careful assessment first. Number of visits and timeline Usually two visits over a few weeks: preparation and impressions, then fitting. Several stages over a few months: placement, a healing period while the post integrates with the bone, then the final crown. CDCP coverage Crowns are a service the Canadian Dental Care Plan can cover for eligible patients, subject to the plan’s rules and preauthorization. Dental implants are not covered by the Canadian Dental Care Plan. How to choose Ask one question first: can this tooth be predictably saved? If yes, a crown protects it and is the simpler, faster treatment. If the tooth is gone or unsavable, an implant rebuilds it without leaning on the neighbours. The cost of each depends on factors such as the tooth’s position, whether a root canal or bone grafting is needed, and the materials chosen — which is why we quote exactly, in writing, after an examination rather than publishing figures that cannot fit your case. Eagle Family Dentistry offers consultations for dental implants, orthodontic treatment and Invisalign in Newmarket — the visit covers an assessment and a discussion of your options. Same-day emergency appointments are available on open days when you call ahead. Call (905) 836-6111. Background reading: the Canadian Dental Association and the federal CDCP page. Common questions
Braces vs Clear Aligners in Newmarket: An Honest Comparison for Families

Braces vs clear aligners in Newmarket is the question almost every family asks at an orthodontic consultation. Both straighten teeth. They differ in discipline, diet, sports, and which movements they handle well. This comparison is written for parents and adult patients at Eagle Family Dentistry, and it is honest about who each system does not suit. It supports our orthodontic care in Newmarket page, where you can read about assessment and treatment planning in more detail. What each option is Side-by-side comparison How to choose Factors that affect cost FAQs Sources and further reading What each option is Braces use brackets bonded to the teeth and a wire that is adjusted over time to guide movement. They work around the clock because they cannot be removed. Clear aligners are a series of transparent, removable trays, changed every week or two, that nudge teeth in small steps. They only work while they are in the mouth — which means most of the day, every day. Both approaches end with retainers; teeth that are not retained will drift, whichever system moved them. Side-by-side comparison: braces vs clear aligners Question Braces Clear aligners What it is / how it works Fixed brackets and wires, adjusted at appointments, applying continuous force day and night. Removable transparent trays worn about 22 hours a day, changed in sequence to move teeth step by step. Typical lifespan Orthodontic results are not a product with a lifespan — they last as long as retainers are worn as directed. Professional guidance from the Canadian Dental Association and orthodontic associations is consistent: retention is lifelong if you want the alignment to hold. The same retention rule applies. Aligners do not hold the final result by themselves; a retainer phase follows treatment, and skipping it is the most common reason aligned teeth shift back. Maintenance and care Brushing and flossing take more effort around brackets and wires; special flossers help. Sticky and very hard foods are avoided to protect the brackets. Trays come out for eating and brushing, so normal hygiene is easier. Trays themselves need daily rinsing and cleaning, and must be stored in their case — not a napkin. Effect on neighbouring teeth and jawbone Moves teeth within the existing bone; complex rotations, vertical movements and bite corrections are handled directly by the fixed system. Also moves teeth within the bone, but some movements — certain rotations and pulling a tooth down — are harder and may need attachments or a different approach. Growing jaws in younger teens add another variable your dentist will assess. Who it suits and who it does not Suits complex cases, younger patients, and anyone who knows they would not wear a removable tray faithfully. It does not suit patients unwilling to adapt eating habits or oral hygiene around brackets. Suits motivated teens and adults with mild to moderate crowding who value discretion and removable trays. It does not suit patients who will leave trays out for long stretches — the treatment simply stalls — or some complex bite problems. Number of visits and timeline Adjustment visits roughly every 6 to 8 weeks; many cases run about 18 to 24 months, though simpler and more complex cases fall outside that range. Check visits roughly every 6 to 10 weeks; timelines are similar for comparable cases, but missed wear stretches the calendar, because teeth only move when trays are worn. CDCP coverage Orthodontic treatment, including braces, is not covered by the Canadian Dental Care Plan. Clear aligners are orthodontic treatment and are likewise not covered by the Canadian Dental Care Plan. How to choose Be honest about habits first. A removable system in the hands of a forgetful wearer loses to a fixed system every time. Then look at the movements your teeth actually need: your assessment includes an examination and imaging, and some bites genuinely need the control of braces, while many crowding cases can be treated either way. Lifestyle matters too — contact sports, wind instruments, public-facing work, and how a teen feels about visible brackets all count. At Eagle, orthodontic treatment is provided by our general dentists; where a case needs a registered specialist, we will say so and arrange a referral rather than stretch a case beyond what we should treat. Same-day emergency appointments are available on open days if an orthodontic problem — a poking wire, a lost tray with pain — cannot wait; call ahead to confirm the day’s availability. Factors that affect cost We do not publish prices, because the honest figure depends on case complexity, treatment length, and whether both arches are treated. Many major insurance plans include some orthodontic coverage — your own plan’s rules decide, and we will help you check. You receive an exact written quote before treatment begins. Call Eagle Family Dentistry in Newmarket at (905) 836-6111 to book an assessment. Frequently asked questions Sources and further reading
How Long Do Dental Implants Take? A Realistic Timeline, Start to Finish

“How long do dental implants take?” is usually the second question Newmarket patients ask us — right after whether they are a candidate at all. The honest answer is a range, not a date: most implant treatments take several months from the first assessment to the final crown, because the longest stage is not an appointment at all. It is the healing your jaw does on its own schedule, and it cannot be rushed without risking the result. This guide walks through each stage, what actually happens at it, and the factors that stretch or shorten the timeline. For the treatment itself — options, candidacy and what placement involves — see our page on dental implant treatment in Newmarket. On this page So, how long do dental implants take, stage by stage? Stage 1: assessment and planning Stage 2: extraction and healing, when a tooth is still there Stage 3: implant placement day Stage 4: osseointegration — the months you can’t rush Stage 5: the crown on top What makes some timelines longer Who is not a candidate right away Frequently asked questions References So, how long do dental implants take, stage by stage? For a straightforward single implant with healthy bone, patients are often looking at roughly three to six months from assessment to final crown. Cases that need a tooth removed first, bone grafting, or a sinus lift can run longer — sometimes nine months or more. The stages below explain where that time actually goes, so a longer estimate reads as a plan rather than a delay. Stage 1: assessment and planning Everything starts with an examination and imaging. Your dentist checks the gap or failing tooth, the health of your gums, and — with 3D or X-ray imaging — the amount and quality of bone where the implant would go. This is also where medical history matters: conditions and medications that affect healing shape the plan. At Eagle Family Dentistry, the consultation for dental implants leaves you with a staged plan and a realistic timeline for your case — confirmed in person, never guessed from a website. Stage 2: extraction and healing, when a tooth is still there If the tooth being replaced is still present and cannot be saved, it is removed first. Sometimes an implant can be placed at the same visit as the extraction; often the socket is left to heal for a period first, because placing an implant into a stable, healthy site gives it a better foundation. Which route fits depends on infection, bone condition and how the tooth comes out — decided at the assessment, not promised in advance. Our page on extraction before implant placement covers this stage in more detail. Stage 3: implant placement day Placement itself is a single appointment. The titanium implant post is placed into the jawbone under local anaesthesia; nitrous oxide is available at our clinic for patients whose anxiety needs additional support, and it is the only form of sedation we offer. Most patients manage the days after with ordinary aftercare and over-the-counter measures as directed. You will usually leave with a plan to protect the site while it heals — and, where appearance matters, a temporary solution for the gap. Stage 4: osseointegration — the months you can’t rush After placement, the bone gradually bonds to the implant surface. This process, called osseointegration, is what makes an implant stable enough to chew on — and it typically takes a few months. There is no honest way to shortcut it: loading an implant before the bone has integrated is one of the more reliable ways to make it fail. During this stage you are mostly just living your life, with periodic checks that healing is on track. Stage 5: the crown on top Once the implant is stable, the visible tooth is made: impressions or scans are taken, and a custom crown is fitted onto the implant. This finishing stage usually takes a few weeks including the laboratory work. The crown is designed to match the shape and shade of your neighbouring teeth and to be cleaned like a natural tooth. What makes some timelines longer Bone grafting. If the jaw has shrunk where a tooth was lost, grafting rebuilds enough bone to hold an implant — and grafts need their own healing time before or alongside placement. Our bone grafting in Newmarket page explains when this step is recommended. Sinus considerations. Upper back teeth sit close to the sinus; sometimes the bone there needs to be built up before an implant can be placed safely. Health and habits. Smoking, uncontrolled diabetes and gum disease all slow healing or raise risk. Sometimes the right first step is treating gum disease or pausing to address a health factor — which lengthens the calendar but protects the outcome. Who is not a candidate right away Not everyone can start immediately, and a clinic that tells you that is doing you a service. Active gum infection, insufficient bone that cannot be rebuilt, or health conditions that make surgery unwise can all mean “not yet” or “not this option.” Alternatives — a bridge, a denture, or staged treatment that addresses the barrier first — should be discussed openly at the assessment. Treatment at Eagle is provided by our general dentists, Dr. Saeed Meshksar and Dr. Meysam Jahanmehr; if a case needs a specialist’s involvement, we will say so. If you want a timeline for your own case rather than a general one, book an implant consultation by calling Eagle Family Dentistry at (905) 836-6111. Frequently asked questions References
دندانپزشک فارسیزبان در نیومارکت: راهنمای کامل خدمات، بیمه و CDCP برای خانوادهها

پیدا کردن دندانپزشک فارسیزبان در نیومارکت که بتوانید با او راحت و به زبان خودتان صحبت کنید، نیمی از مسیر درمان است. وقتی درد دارید، وقتی قرار است درمانی برای فرزندتان توضیح داده شود، یا وقتی میخواهید بدانید بیمهتان دقیقاً چه چیزی را پوشش میدهد، زبان نباید یک مانع اضافه باشد. این راهنما برای خانوادههای فارسیزبان نیومارکت و اطراف آن نوشته شده است: چه خدماتی در کلینیک دندانپزشکی ایگل (Eagle Family Dentistry) ارائه میشود، بیمه و برنامهٔ CDCP چطور کار میکند و چه چیزهایی را پوشش نمیدهد، مشاورهٔ رایگان ایمپلنت و ارتودنسی یعنی چه، و در اولین ویزیتتان چه اتفاقی میافتد — قدمبهقدم و بدون ابهام. چرا انتخاب دندانپزشک فارسیزبان مهم است درمان دندانپزشکی فقط پر کردن و کشیدن دندان نیست؛ تصمیمهایی است که باید با اطلاعات کامل بگیرید. وقتی توضیحات را به زبان خودتان میشنوید: در ایگل، دکتر میثم جهانمهر و تیم ما فارسی صحبت میکنند. همانطور که در صفحهٔ اصلی کلینیک هم نوشتهایم: «ما به فارسی صحبت میکنیم! دکتر میثم جهانمهر و تیم ما با کمال میل به زبان فارسی پاسخگوی شما هستند.» اگر میخواهید اول با کلینیک و تیم ما بیشتر آشنا شوید، از صفحهٔ فارسی کلینیک ایگل در نیومارکت شروع کنید؛ این راهنما بخش عملی ماجراست: خدمات، بیمه و اولین ویزیت. چه خدماتی در ایگل ارائه میشود ایگل یک کلینیک دندانپزشکی عمومی خانوادگی است؛ یعنی بیشتر نیازهای دندانی همهٔ اعضای خانواده — از کودک تا سالمند — در یک جا بررسی و درمان میشود. دکتر میثم جهانمهر و دکتر سعید مشکسار، دندانپزشکان عمومی کلینیک هستند. خدمات ما شامل اینهاست: اگر موردی نیاز به درمان تخصصی پیچیده داشته باشد، صادقانه به شما میگوییم و در صورت نیاز، شما را به متخصص مربوطه ارجاع میدهیم. هیچ خدمتی را که انجام نمیدهیم، به نام خودمان تبلیغ نمیکنیم. بیمه و CDCP چطور کار میکند — چه چیزهایی پوشش داده میشود و چه چیزهایی نه بیمههای خصوصی و کاری. اگر از محل کار یا بهصورت شخصی بیمهٔ دندان دارید، مشخصات بیمهتان را همراه بیاورید یا هنگام گرفتن نوبت به ما بدهید تا قبل از شروع درمان، پوشش و سهم پرداختی شما تا حد امکان روشن شود. قانون کلی ما ساده است: هزینهٔ درمان را پزشک در ویزیت و پس از معاینه تأیید میکند — قبل از اینکه درمانی شروع شود، میدانید قرار است چه اتفاقی بیفتد. برنامهٔ مراقبت دندانی کانادا (CDCP). این برنامهٔ دولت فدرال برای ساکنان کاناداست که به بیمهٔ دندان دسترسی ندارند و درآمد خالص تعدیلشدهٔ خانوادهشان کمتر از ۹۰٬۰۰۰ دلار است. واجد شرایط بودن را خود برنامه تأیید میکند — بر اساس اظهارنامهٔ مالیاتی و نداشتن دسترسی به بیمه — و ثبتنام از طریق دولت انجام میشود، نه کلینیک. جزئیات رسمی را در برنامهٔ مراقبت دندانی کانادا (CDCP) در وبسایت دولت کانادا ببینید؛ برای خدمات CDCP در نیومارکت هم صفحهٔ اختصاصی ما را بخوانید: خدمات CDCP در نیومارکت. اگر عضو CDCP باشید، برنامه برای بسیاری از خدمات پایه و درمانی — مثل معاینه، عکسبرداری، جرمگیری، پر کردن، عصبکشی و کشیدن دندان — درصدی از هزینههای تعیینشدهٔ خودش را میپردازد. دو نکتهٔ صادقانه را از اول بدانید: برای بعضی خدمات هم برنامه قبل از درمان تأییدیه میخواهد (پیشتأیید)؛ تیم ما در ویزیت توضیح میدهد که برای درمان شما چه مراحلی لازم است. مشاورهٔ رایگان برای ایمپلنت و ارتودنسی: یعنی چه در ایگل، مشاوره برای سه خدمت رایگان است: ایمپلنت دندان، ارتودنسی و اینویزیلاین. «مشاورهٔ رایگان» یعنی در آن جلسه: این مشاوره فقط برای همین سه خدمت است؛ برای بقیهٔ خدمات، شرایط ویزیت را هنگام گرفتن نوبت از ما بپرسید. برای آشنایی بیشتر با جایگزینی دندان ازدسترفته، صفحهٔ ایمپلنت دندان در نیومارکت و برای مرتب کردن دندانها، صفحهٔ ارتودنسی و اینویزیلاین در نیومارکت را ببینید. تصمیم نهایی همیشه بعد از معاینه گرفته میشود — مشاوره یعنی اطلاعات کامل، نه تعهد به شروع درمان. اولین ویزیت شما قدمبهقدم اگر اولین بار است که به ایگل میآیید، این ترتیب را انتظار داشته باشید: برای اولین ویزیت نزد دندانپزشک فارسیزبان در نیومارکت اینها را همراه داشته باشید: کارت بیمه (اگر دارید)، اطلاعات عضویت CDCP (اگر عضو هستید)، فهرست داروهای مصرفی، و اگر از کلینیک دیگری میآیید، هر عکس یا سابقهای که در دسترس دارید. چطور نوبت بگیریم برای گرفتن نوبت یا پرسیدن هر سؤالی، با کلینیک دندانپزشکی ایگل در نیومارکت تماس بگیرید: (905) 836-6111— میتوانید فارسی صحبت کنید. از طریق صفحهٔ تماس با ما هم میتوانید پیام بگذارید. اگر تازه به کانادا یا نیومارکت آمدهاید و هنوز دندانپزشکی ندارید، قدم اول فقط یک تماس است. ما شرایطتان را میشنویم، دربارهٔ بیمه یا CDCP راهنماییتان میکنیم و اولین ویزیت را طوری تنظیم میکنیم که با خیال راحت شروع کنید. منابع راهنماییهای این مقاله بر اساس منابع آموزش و اطلاعرسانی دندانپزشکی کانادا از ، و تنظیم شده است. دندانپزشکان انتاریو تحت نظارت RCDSO فعالیت میکنند و میتوانید اعتبار و وضعیت ثبت هر دندانپزشک را در وبسایت RCDSO بررسی کنید. جزئیات برنامهٔ CDCP — شرایط، ثبتنام و پوششها — از صفحات رسمی دولت کانادا (Canada.ca) گرفته شده است؛ اگر تفاوتی میان این راهنما و Canada.ca بود، مرجع درست Canada.ca است، چون قواعد برنامه ممکن است تغییر کند.Royal College of Dental Surgeons of Ontario (RCDSO)Canadian Dental AssociationOntario Dental Association پرسشهای پرتکرار خانوادههای فارسیزبان
Cracked a Tooth? Why a Crown Is Often the Thing That Saves It
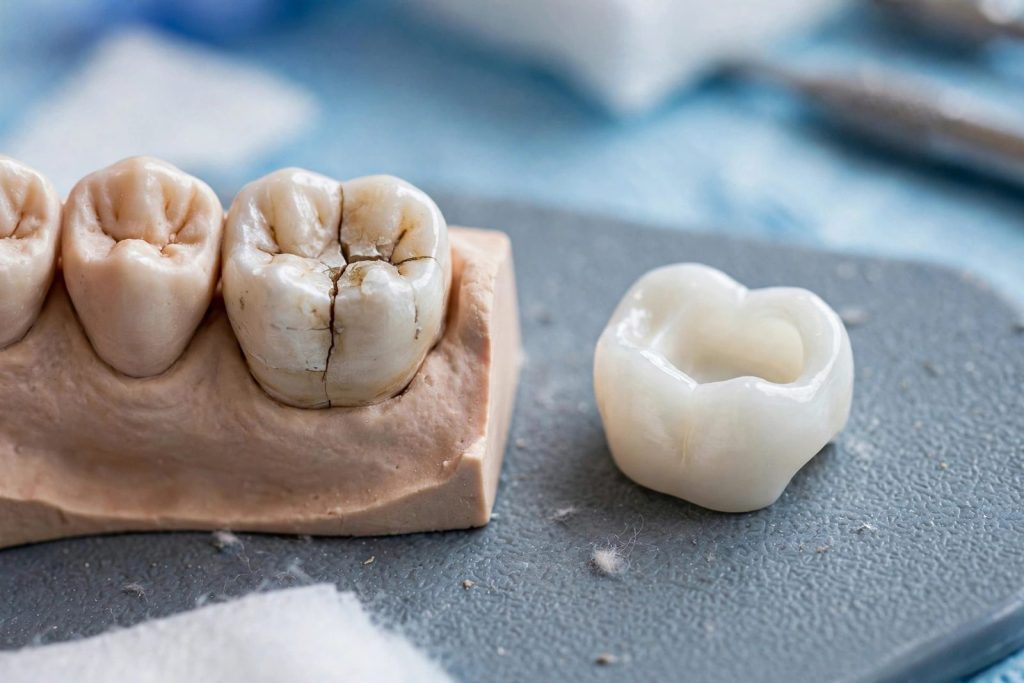
It usually starts with something small. A sharp twinge when you bite down on something crunchy. A rough edge your tongue keeps finding. Or nothing you can feel at all — just your dentist pausing during a checkup to say, “There’s a crack in this tooth.” A cracked tooth is one of the most common reasons a crown gets recommended, and one of the most confusing. Does a crack always need a crown? Can it wait? What happens if you leave it? This guide answers those questions the way we’d want them answered honestly: how teeth crack, how to tell a crack from a chip, the signs a crack is getting worse, and when a crown genuinely is the thing that saves the tooth — plus the cases where a crown is not enough. If you’re in Newmarket and you’ve just been told you have a cracked tooth, start here, then bring your questions to an assessment. How Teeth Crack (and Why It Often Happens Silently) Teeth are strong, but they are not unbreakable, and they flex a tiny amount every time you chew. Over years, that everyday stress adds up — especially on teeth that already carry large fillings, because a big filling leaves less natural tooth structure to absorb the force. The most common causes of cracks: Why “silently”? A crack doesn’t always hurt, and hairline cracks can be invisible on the surface and hard to spot even on an X-ray. Many cracks are found during a routine exam, or only once they deepen enough to start flexing when you bite — which is when the classic symptom, a sharp pain on biting or on releasing the bite, shows up. A crack that is silent today is not necessarily stable: cracks do not heal, and they tend to extend under load. That is why the plan for a cracked tooth is based on where the crack is, how deep it runs, and whether the nerve is involved — all of which an assessment with imaging can show. Cracked Tooth vs. Chipped Tooth vs. Broken Cusp — What’s the Difference? These three get mixed up constantly, and they are not the same problem: The practical difference: chips and broken cusps are about missing structure; cracks are about compromised structure that is still there but failing. That is exactly the situation a crown is designed for — it holds the remaining tooth together. Whether your tooth has a chip, a broken cusp or a true crack decides the treatment, and it often can’t be judged from a photo or a description. It takes an exam, sometimes with magnification and imaging. Signs Your Crack Is Getting Worse A stable, shallow crack under review is one thing. These signs mean the crack — or the nerve inside the tooth — is progressing, and the tooth should be seen promptly rather than watched: One honest warning: a tooth that stops hurting after weeks of symptoms has not necessarily healed. It can mean the nerve has died — after which infection can develop quietly at the root tip. If a cracked tooth goes silent after being symptomatic, it still needs to be assessed. If you have swelling, fever, or pain you can’t manage, treat it as urgent and call (905) 836-6111 the same day. Why a Crown Protects What’s Left A dental crown is a custom-made cap that covers the entire visible part of the tooth. For a cracked tooth, its job is mechanical: it binds the tooth together so the crack can’t flex open every time you bite. Think of it as a splint that never comes off — chewing forces are spread over the whole covered tooth instead of concentrating at the crack line. That protection does two things. First, it stops the crack from being pried wider with every meal, which is how most cracks eventually split a tooth in two. Second, it seals the tooth, keeping bacteria out of the crack and away from the nerve. A crown also restores the tooth’s shape, so you can chew on it normally again. What a crown does not do is heal the crack. The fracture line is still in the tooth underneath; the crown protects it from the forces that would extend it. That distinction is why diagnosis comes first — a crown is the right protection when enough sound tooth remains to hold it, and the wrong plan when the crack has already gone too far (next section). For the full picture of how crowns work and what they’re made from, see our page on dental crown treatment in Newmarket. When a Crown Is NOT Enough (Root Canal First, or Extraction) Honesty matters here, because a crown is not the answer to every cracked tooth: None of these can be decided from symptoms alone. At the assessment, your dentist examines the tooth, tests the bite and the nerve, and reviews imaging to see how far the crack extends. Sometimes the honest answer is “crown it and monitor”; sometimes it is “root canal, then crown”; occasionally it is “this tooth can’t be saved.” A good treatment plan names which one — and why — before any work begins. What the Crown Process Involves, Visit by Visit The exact sequence is confirmed at your assessment — including how many visits your case needs and which crown approach suits the tooth. In general, the process looks like this: Visit one — assessment and preparation. Your dentist confirms the diagnosis, examines the crack, and reviews X-rays. If a crown is the plan, the tooth is numbed with local anaesthesia, shaped so the crown can fit over it, and scanned or moulded so the crown can be made to match your bite and the neighbouring teeth. If the tooth will be without its final crown for a period, a temporary crown protects it in the meantime — it looks like a tooth and keeps the prepared tooth safe, but it is not made for heavy-duty
Every Six Months — or Is It Just a Saying? How Often You Really Need a Cleaning
Ask ten people how often you should get your teeth cleaned and most will give you the same answer without thinking: every six months. It’s one of those rules everyone knows — but where did it come from, and is it actually the right schedule for your mouth? The honest answer is that six months is a reasonable default for many people, but it was never a law of nature. Modern dental guidance sets your cleaning interval individually, based on the health of your gums, how quickly tartar builds up on your teeth, and your personal risk factors. Some people genuinely need to come in every three or four months; others can safely go longer. This guide explains how that decision is made, what a cleaning appointment actually involves, and how programs like the CDCP and workplace insurance fit into the schedule — so you can tell whether your current routine is right for you. Where the “Every 6 Months” Idea Came From The twice-a-year habit is older than the science behind it. It took hold in the early-to-mid twentieth century — spread through hygiene advice and, famously, toothpaste advertising — and it stuck because it was simple, memorable, and a workable rhythm for the average mouth. What it was not based on was a study that tested six months against nine or twelve and proved six the winner. When researchers have reviewed the evidence since, they have not found strong support for one fixed interval that suits everyone. That’s why dental associations and practising dentists increasingly describe recall visits the same way: the interval should be set for the individual, after an assessment, and reviewed as your health changes. For a lot of adults, that individual answer still lands on about every six months — which is why the saying survives. But for the people in the next sections, it lands somewhere else, in both directions. So treat “every six months” as a starting question, not an answer. The answer comes from what your hygienist and dentist find — which raises a fair question: what exactly are they looking for at a professional teeth cleaning in Newmarket? What Your Hygienist Is Actually Checking (It’s Not Just Polish) A cleaning appointment does more than make your teeth feel smooth. Here’s what the visit actually covers: Removing what brushing can’t. Soft plaque builds up on teeth every day. Given time, it hardens into tartar (also called calculus) — and once plaque has hardened, no amount of brushing or flossing at home will remove it. Your hygienist removes plaque and tartar from above and below the gumline with professional instruments; that removal, called scaling, is the core of the appointment. Checking your gums. The hygienist looks for bleeding, swelling and pockets forming between tooth and gum — the early signs of gum disease. Early gum inflammation (gingivitis) is reversible; catching it at this stage is one of the main reasons the interval matters. Screening the whole mouth. Soft tissues — cheeks, tongue, palate — are checked for anything unusual, and your teeth for wear, cracks and failing fillings. Polishing and stain removal. The polish at the end removes surface stain from coffee, tea and tobacco and leaves teeth smoother, which makes them a little harder for new plaque to grip. Updating your home-care game plan. Expect specific feedback: the spots you’re missing, whether a different brush or interdental tool would help, and fluoride advice where it’s relevant. In other words, a cleaning is partly treatment and partly surveillance. The right interval is the one that keeps the surveillance ahead of the problems — and that depends on how fast things change in your mouth. Who Genuinely Needs More Frequent Cleanings For the following situations, dentists commonly recommend a shorter interval — often every three to four months — because plaque, tartar and inflammation move faster than a six-month cycle can catch: You have had gum disease. After treatment for periodontitis, maintenance visits at shorter intervals help keep the disease from re-establishing itself in the pockets around your teeth. This is probably the most common reason for a three-to-four-month schedule. You have diabetes. Diabetes and gum disease influence each other — gum inflammation is harder to control, and infections can be slower to settle — so closer monitoring of your gums is usually part of good care. You smoke or vape. Tobacco use raises gum-disease risk and dulls the warning signs (like bleeding) that would otherwise be noticed early. You wear braces or other orthodontic appliances. Brackets and wires trap plaque in places a brush struggles to reach, so more frequent professional cleaning helps protect teeth while they move. You’re pregnant. Hormonal changes can make gums react more strongly to plaque — the familiar “pregnancy gingivitis” — so your dentist may suggest keeping visits closer together during pregnancy. You have dry mouth. Saliva protects teeth; many medications and some conditions reduce it, and less saliva means cavities start faster. More frequent checks and fluoride support are commonly recommended. You build tartar quickly or have a history of frequent cavities. Some mouths simply mineralize plaque faster than others. If that’s you, your hygienist already knows — it’s in your chart, and it drives your interval. None of these is a life sentence to a fixed schedule. Intervals get reviewed at each visit, and if your gums stay healthy, your dentist may lengthen the gap again. Who May Safely Go Longer The individual approach cuts both ways. If you are an adult with healthy gums, no history of gum disease, a low cavity rate, and home care that’s genuinely working, your dentist may suggest stretching your recall to nine or twelve months. That’s not cutting corners — it’s the same risk-based logic, applied in the other direction. Two cautions, though. First, “low risk” is an assessment, not a self-diagnosis: the things that make someone high-risk (early gum pockets, fast tartar buildup, new medications causing dry mouth) often have no symptoms you’d notice at home.
Scared of the Dentist? You’re Not Alone — Here’s How a Gentle Visit Actually Works

If the thought of sitting in a dental chair makes your stomach knot — if you’ve cancelled appointments, put off a toothache, or simply stopped going — you are not unusual, and you are not the problem. Dental anxiety is one of the most common reasons adults avoid care, and it usually has a perfectly understandable cause: a bad experience, a fear of needles or pain, worry about being judged for the state of your teeth, or just the feeling of not being in control. This guide explains what a gentle dentist in Newmarket actually does in practice — not as a slogan, but as a set of concrete things a dental team can do differently, including how nitrous oxide (laughing gas) works and what it honestly can’t do. It also walks through what a first visit looks like if you’re anxious, and how the conversation changes when you simply tell us you’re nervous. Why Dental Anxiety Is So Common (and Nothing to Be Embarrassed About) Dental fear is studied, documented and extremely common — surveys of adult patients consistently find that a large share feel some anxiety about dental treatment, and a smaller share avoid the dentist because of it. It tends to come from a handful of sources: A past experience that hurt or felt rushed — one bad appointment can colour every visit after it. Fear of needles or of pain — for many people the injection, not the treatment, is the worst part. Loss of control — lying back while someone works in your mouth, unable to talk, is an unusual position to be in. Embarrassment — worry about being lectured about your teeth, your habits or how long it’s been. Sounds, smells and sensations — the drill’s noise and vibration unsettle people who are otherwise calm. None of these make you a difficult patient. They make you a normal one. A dental team that sees anxious patients every week expects this conversation, and the rest of this guide is about what can actually be done about each of these causes. What “Gentle Dentistry” Actually Means in Practice “Gentle” shouldn’t be a word a clinic just prints on its website. In practice, it is a set of habits and choices you can hold any dental team to: You are told before anything happens. Each step is explained before it starts — what it is, what you will feel, and how long it takes — so nothing arrives as a surprise. You have a stop signal. Before treatment begins, you agree on a signal (usually raising a hand) that means “pause, now.” The team stops, you sit up, you take a breath, and nothing continues until you’re ready. Numbing is done slowly and in stages. The area is numbed with local anesthetic so treatment itself is comfortable; a numbing gel is applied to the gum first so the injection is felt as little as possible, and the anesthetic is given slowly rather than rushed. The pace is yours. Breaks are normal, appointments can be kept shorter, and larger treatment plans can be split into smaller visits so no single day feels overwhelming. No lectures, no judgment. However long it has been and whatever state your teeth are in, the job of the visit is to assess and plan — not to scold. You will hear what we find and what we recommend, in plain language. Help for anxiety is part of the plan, not an afterthought. For patients who want it, nitrous oxide can be part of most appointments — including checkups and cleanings, not only bigger procedures. These habits apply across the dental services we provide in Newmarket — they aren’t a special package. They’re how anxious patients should expect to be treated everywhere in the clinic. How Nitrous Oxide (Laughing Gas) Works — and What It Does Not Do Nitrous oxide is a mild sedative gas, mixed with oxygen, that you breathe through a small mask over your nose during your appointment. It has been used in dentistry for well over a century precisely because it is gentle, adjustable and short-lived. Here is the honest version of how it works: What it feels like: within a few minutes most people feel calmer, lighter and less focused on what’s happening. You may feel a mild tingling or floaty sensation. The level can be adjusted up or down during the appointment. You stay awake. Nitrous oxide does not put you to sleep. You remain aware, you can hear and respond to the team, and you can use your stop signal at any point. It takes the edge off anxiety — it doesn’t remove you from the appointment. It does not numb your teeth. Nitrous handles the anxiety; local anesthetic handles the numbing. The two do different jobs and are often used together. It wears off within minutes. Once the mask comes off and you breathe oxygen, the gas clears your system quickly. Because it leaves so fast, most patients feel back to normal shortly after the appointment and can drive themselves home — the team will always check that you feel fully yourself before you leave. It’s the only sedation we offer — and we’ll say so plainly. At Eagle Family Dentistry, sedation means nitrous oxide. We do not offer IV sedation or general anesthesia. For the large majority of anxious patients, nitrous plus the approach described here is enough to get needed care done comfortably. If a situation ever called for more than nitrous can provide, we would tell you honestly and discuss referral options rather than oversell what we do. It isn’t automatic for everyone. Suitability is assessed from your medical history — for example, if you can’t breathe comfortably through your nose, have certain respiratory conditions, are in the first trimester of pregnancy, or take certain medications, the team may advise against it or adjust the plan. That’s a conversation at your visit, not a formality. If your anxiety is specifically about having
Dental Implant vs Bridge: Which Is Better for a Missing Tooth?
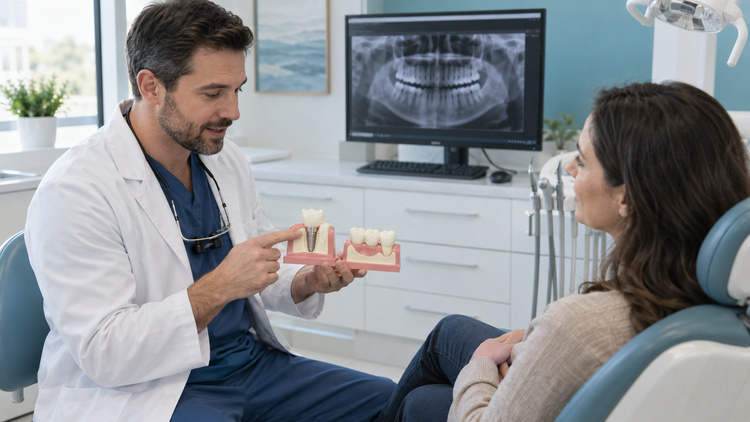
When comparing a dental implant vs bridge for a missing tooth, neither option is automatically the better choice. A dental implant replaces the missing tooth root and supports a separate replacement tooth, while a traditional dental bridge fills the gap by using neighbouring teeth for support. The right option depends on the health of the adjacent teeth, available jawbone, your general health, treatment preferences, maintenance needs and budget. If the teeth beside the gap are healthy, a dental implant may allow them to remain untouched. A bridge does not require implant surgery, but a traditional bridge normally requires the supporting teeth to be prepared for crowns. A dental examination and appropriate X-rays are needed before deciding which approach is suitable. Dental Implant vs Bridge: Quick Comparison Factor Dental Implant Traditional Dental Bridge How the replacement is supported An implant is placed in the jawbone and supports the replacement tooth The replacement tooth is supported by neighbouring teeth Adjacent teeth Usually does not require preparing healthy neighbouring teeth Supporting teeth are generally prepared for crowns Surgery Requires implant placement surgery Does not require implant surgery Jawbone Adequate bone is needed, although bone grafting may sometimes be possible Does not require bone to support an implant Treatment stages Usually involves several stages and a healing period Commonly involves preparation, impressions or scanning, a temporary restoration and placement of the final bridge Cleaning Requires brushing, cleaning around the implant and regular dental care Requires cleaning around and underneath the bridge as well as the supporting teeth Best choice Depends on the condition of your teeth, gums, bone, health and treatment priorities What Is a Dental Implant? A dental implant is an artificial tooth root, typically made from titanium, that is placed into the jawbone. After the implant has integrated with the surrounding bone, an abutment and replacement tooth can be attached. The Canadian Dental Association notes that implants can be used to replace missing roots and support artificial teeth. Implant treatment usually involves an assessment, surgical placement, healing and placement of the final restoration. Learn more about dental implants in Newmarket. When patients weigh a dental implant vs bridge, the implant’s biggest advantage is that it stands on its own, without relying on the teeth beside the gap. What Is a Dental Bridge? A dental bridge is a fixed restoration that replaces one or more missing teeth by spanning the gap. In a traditional tooth-supported bridge, the artificial tooth is connected to crowns placed over the neighbouring teeth. According to the Canadian Dental Association, the teeth beside the missing tooth are typically prepared before the bridge is made and cemented into place. Other bridge designs, including resin-bonded, cantilever and implant-supported bridges, may be considered in specific situations. Learn more about dental bridges in Newmarket. In a dental implant vs bridge comparison, the bridge is often the faster route, since it does not involve surgery or a healing period before the final tooth is placed. How Do Dental Implants and Bridges Differ? 1. Effect on the Teeth Beside the Gap One of the main differences is how the restoration receives support. A single dental implant is supported by the implant itself. It usually does not require healthy teeth beside the space to be reshaped. A traditional bridge generally relies on teeth beside the gap. The Canadian Dental Association explains that these supporting teeth are prepared for the crowns that hold the bridge in place. This difference can be particularly important when both neighbouring teeth are healthy and have little or no previous restorative work. 2. Surgery and Treatment Process Dental implant placement is a surgical procedure. The implant is positioned in the jawbone and needs time to heal and integrate before the final replacement tooth can be completed. The Canadian Dental Association notes that implant healing can take several months and that several appointments may be required. A traditional bridge does not require implant surgery. The supporting teeth are prepared, an impression or digital scan is taken and a temporary bridge may be used while the final restoration is made. The actual timeline for either option varies according to the condition of the mouth, treatment complexity and any additional procedures required. 3. Jawbone Requirements An implant needs enough healthy bone for support. Your dentist assesses the area clinically and with appropriate imaging before recommending implant placement. If the jawbone has reduced in volume, implant treatment is not automatically ruled out. In some cases, bone grafting may be considered to improve the available bone before or during implant treatment. A traditional tooth-supported bridge does not need jawbone to hold an implant because the restoration is anchored to neighbouring teeth. However, the supporting teeth and gums still need to be suitable for the restoration. 4. Bone Around the Missing Tooth A natural tooth root transmits forces to the surrounding jawbone. When a tooth is lost, changes in the bone can occur over time. A single-tooth implant replaces the missing root as well as supporting the visible replacement tooth. The American Academy of Periodontology notes that this can help preserve bone in the missing-tooth area. A conventional bridge replaces the visible tooth but does not place a root replacement into the empty socket. 5. Cleaning and Maintenance Neither option is maintenance-free. Dental implants need consistent brushing, cleaning between the teeth and professional monitoring. The gums and tissues around an implant can develop problems if plaque is not controlled. With a bridge, the supporting teeth require careful cleaning and the area beneath the artificial tooth also needs to be cleaned. Your dental team may recommend a floss threader, interdental brush or another device depending on the bridge design. 6. Repair and Replacement Over Time Both implants and bridges require ongoing dental care, and neither should be described as permanent for every patient. The Canadian Dental Association states that a well-cared-for bridge can generally last about 10 years or longer. Its lifespan can be affected by the condition of the supporting teeth, decay, gum health, bite forces and
Dental Bridge Cleaning: 6 Questions for Your Newmarket Dentist

Dental bridge cleaning needs a routine that reaches the spaces around your bridge. For Newmarket patients, a demonstration can make everyday care easier to understand.